Просмотр новости
Найдите то, что Вас интересует
 Спутники
 РН
 SpaceX
 Роскосмос
 NASA
СпутникиРНSpaceXРоскосмосNASAIntroduction Stroke is a primary contributor to global adult morbidity, frequently resulting in debilitating gait disturbances that impede independence. While standard neurorehabilitation remains essential, the advent of robot-assisted gait training (RAGT) provides a platform for high-intensity, reproducible interventions designed to stimulate neuroplasticity. This systematic review evaluated the literature from 2015 to 2025 to determine the influence of RAGT on neural reorganization and functional outcomes in stroke survivors. Methodology A systematic search of MEDLINE, PubMed, Scopus, and Cochrane Library was performed for studies published between 2015 and 2025. The inclusion criteria were randomized controlled trials, systematic reviews, and meta-analyses investigating RAGT in acute, subacute, and chronic stroke patients. The evaluation metrics included clinical functional scales (e.g., the Berg Balance Scale and the 10-Meter Walk Test) and neurophysiological markers (e.g., fMRI, fNIRS, QEEG, and BDNF). Results Analysis of 23 randomized trials and multiple meta-analyses indicated that RAGT combined with conventional therapy yielded significant improvements in gait speed (standardized mean difference [SMD] = 0.47) and balance (mean difference [MD] = 4.58). Neuroimaging revealed increased activation of the primary motor cortex and supplementary motor areas. Electrophysiological data confirmed reductions in the Power Ratio Index, suggesting normalized cortical activity. End-effector systems have demonstrated superior efficacy in the subacute phase compared to exoskeletons. Conclusion RAGT serves as a potent driver of cortical and spinal neuroplasticity by facilitating high-repetition task-specific stimuli. Early intervention during the subacute phase maximizes functional recovery. Future research should prioritize standardizing the dosing and longitudinal monitoring of neural connectivity. Trial Registration Status: Not Applicable.

ALL Metrics
-
Views
Manickavasagam I, Srinivasan V, Durairaj S et al. Robotic Training and Neural Reorganization in Stroke: A Systematic Review [version 1; peer review: 2 approved]. F1000Research 2026, 15:762 (https://doi.org/10.12688/f1000research.180596.1)
▬
✚
Systematic Review
[version 1; peer review: 2 approved]
Iyyappan Manickavasagam1,2, Vignesh Srinivasan1, Satheeskumar Durairaj
https://orcid.org/0000-0002-6962-8168
3, Animesh Hazarihttps://orcid.org/0000-0002-3936-5029
3, Praveen Kumar Kanadakurtihttps://orcid.org/0000-0003-2669-4488
3Iyyappan Manickavasagam1,2, Vignesh Srinivasan1, [...] Satheeskumar Durairaj
https://orcid.org/0000-0002-6962-8168
3, Animesh Hazarihttps://orcid.org/0000-0002-3936-5029
3, Praveen Kumar Kanadakurtihttps://orcid.org/0000-0003-2669-4488
3PUBLISHED 19 May 2026
1 Saveetha College of Physiotherapy, Saveetha Institute of Medical & Technical Science (SIMATS), SIMATS Deemed University, Chennai, Tamil Nadu, India
2 Dubai Health, Dubai Physiotherapy and Rehabilitation Center, Dubai, United Arab Emirates
3 College of Health Sciences, Gulf Medical University, Ajman, Ajman, United Arab Emirates
Iyyappan Manickavasagam
Roles: Conceptualization, Investigation, Methodology, Writing – Original Draft Preparation, Writing – Review & Editing
Vignesh Srinivasan
Roles: Conceptualization, Data Curation, Formal Analysis, Supervision, Writing – Original Draft Preparation, Writing – Review & Editing
Satheeskumar Durairaj
Roles: Conceptualization, Data Curation, Methodology, Writing – Original Draft Preparation, Writing – Review & Editing
Animesh Hazari
Roles: Conceptualization, Data Curation, Formal Analysis, Writing – Original Draft Preparation, Writing – Review & Editing
Praveen Kumar Kanadakurti
Roles: Conceptualization, Data Curation, Formal Analysis, Project Administration, Writing – Original Draft Preparation, Writing – Review & Editing
OPEN PEER REVIEW
REVIEWER STATUS
Stroke is a primary contributor to global adult morbidity, frequently resulting in debilitating gait disturbances that impede independence. While standard neurorehabilitation remains essential, the advent of robot-assisted gait training (RAGT) provides a platform for high-intensity, reproducible interventions designed to stimulate neuroplasticity. This systematic review evaluated the literature from 2015 to 2025 to determine the influence of RAGT on neural reorganization and functional outcomes in stroke survivors.
MethodologyA systematic search of MEDLINE, PubMed, Scopus, and Cochrane Library was performed for studies published between 2015 and 2025. The inclusion criteria were randomized controlled trials, systematic reviews, and meta-analyses investigating RAGT in acute, subacute, and chronic stroke patients. The evaluation metrics included clinical functional scales (e.g., the Berg Balance Scale and the 10-Meter Walk Test) and neurophysiological markers (e.g., fMRI, fNIRS, QEEG, and BDNF).
ResultsAnalysis of 23 randomized trials and multiple meta-analyses indicated that RAGT combined with conventional therapy yielded significant improvements in gait speed (standardized mean difference [SMD] = 0.47) and balance (mean difference [MD] = 4.58). Neuroimaging revealed increased activation of the primary motor cortex and supplementary motor areas. Electrophysiological data confirmed reductions in the Power Ratio Index, suggesting normalized cortical activity. End-effector systems have demonstrated superior efficacy in the subacute phase compared to exoskeletons.
ConclusionRAGT serves as a potent driver of cortical and spinal neuroplasticity by facilitating high-repetition task-specific stimuli. Early intervention during the subacute phase maximizes functional recovery. Future research should prioritize standardizing the dosing and longitudinal monitoring of neural connectivity.
Trial Registration Status: Not Applicable.
Exoskeleton Device; Recovery of Function; Locomotion; Motor Skills; Neuroplasticity.
Corresponding authors: Satheeskumar Durairaj, Animesh Hazari Competing interests: No competing interests were disclosed.
Grant information: The author(s) declared that no grants were involved in supporting this work.
Copyright: © 2026 Manickavasagam I et al. This is an open access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited. How to cite: Manickavasagam I, Srinivasan V, Durairaj S et al. Robotic Training and Neural Reorganization in Stroke: A Systematic Review [version 1; peer review: 2 approved]. F1000Research 2026, 15:762 (https://doi.org/10.12688/f1000research.180596.1) First published: 19 May 2026, 15:762 (https://doi.org/10.12688/f1000research.180596.1) Latest published: 19 May 2026, 15:762 (https://doi.org/10.12688/f1000research.180596.1)
The global burden of stroke represents one of the most significant challenges to modern healthcare systems, with cerebrovascular accidents serving as the second leading cause of mortality and the third leading cause of long-term motor disability worldwide.1 Among the various sequelae of stroke, gait dysfunction is particularly debilitating, as it fundamentally impairs independence in activities of daily living, restricts social participation, and substantially lowers the perceived quality of life.2 Post-stroke patients often manifest abnormal gait patterns characterized by temporal and spatial asymmetry between steps, reduced propulsion at push-off, and significant postural instability. These deficits are not merely mechanical but reflect a profound disruption of the neural control systems governing locomotion, necessitating a rehabilitation approach that targets the central nervous system’s capacity for reorganization.3,4
Neuroplasticity, defined as the brain’s ability to modify its structural and functional organization in response to environmental demands and injury, is the biological foundation of stroke recovery.5,6 This process encompasses a spectrum of changes, ranging from cellular adaptations—such as synaptic strengthening through long-term potentiation and dendritic sprouting—to macroscopic shifts in cortical representation and the re-establishment of interhemispheric balance.4,6 In the aftermath of a stroke, the brain enters a state of heightened sensitivity to sensorimotor input, particularly during the acute and subacute phases.7,8,9 During this “neuroplastic window,” the implementation of intensive, task-specific, and repetitive training is critical for guiding neural reorganization toward functional recovery rather than maladaptive compensation.
Traditional therapist-assisted gait training, while foundational, is often limited by the physical demands placed on clinicians and the inability to provide the high volume of repetitions necessary to trigger robust plastic changes.5 Evidence from animal models suggests that significant synaptic changes in the motor cortex occur only after hundreds of reach movements, and gait training may require 1,000 to 2,000 steps per session to be truly effective.5 In contrast, conventional human physical therapy sessions often achieve fewer than 360 steps, highlighting a substantial “dosage gap” in current clinical practice.5 Robotic-assisted gait training (RAGT) has emerged as a scalable and technology-enhanced solution designed to address these limitations by enabling the delivery of high-intensity, reproducible, and programmable movement patterns which supports Universal Health Coverage.2
The technological evolution of RAGT systems between 2015 and 2025 has been marked by a transition from passive guidance to “assist-as-needed” paradigms and the integration of multimodal feedback systems.9 These systems are broadly categorized into exoskeleton devices, which move joints along a preprogrammed kinematic trajectory, and end-effector systems, which interact with the patient at the distal end of the limb to simulate natural gait cycles.7 Beyond physical assistance, contemporary RAGT often incorporates virtual reality (VR), gaming interfaces, and real-time sensorimotor analytics, all of which enhance patient engagement and cognitive involvement—elements essential for activating the motor learning circuits of the brain.9,10
While the clinical efficacy of RAGT in improving walking speed and balance has been increasingly validated, the underlying neural mechanisms remain a subject of intense investigation.4 Recent advancements in MRI-compatible robotic devices and portable brain-imaging technologies, such as functional Near-Infrared Spectroscopy (fNIRS) and quantitative Electroencephalography (QEEG), have allowed researchers to observe the cortical and spinal changes induced by robotic therapy in real-time.11 These studies suggest that RAGT facilitates reorganization in both the lesioned and non-lesioned hemispheres, modulates spinal reflex pathways like the H-reflex, and may even influence biochemical markers of plasticity such as Brain-Derived Neurotrophic Factor (BDNF).12,13,14
This systematic review aims to provide a comprehensive synthesis of the literature published from 2015 to 2025 regarding the influence of RAGT on neuroplasticity in stroke patients. By analyzing systematic reviews, meta-analyses, and randomized trials, this report evaluates the functional impact of RAGT, identifies the specific neural pathways modulated by robotic interventions, and explores clinical variables, such as timing, device type, and training intensity, that optimize the neuroplastic response. The findings provide evidence-based guidance for integrating robotic technology into standard stroke rehabilitation protocols and highlight future directions for precision neurorehabilitation.
This systematic review was designed to capture the most significant clinical and technological developments in robotic gait rehabilitation over the past decade. A comprehensive search was conducted across several electronic databases, including MEDLINE, PubMed, the Cochrane Library, Scopus, Web of Science, and Embase.2,9 The search strategy focused on publications released between January 2015, and December 2025, a period characterized by the maturation of robotic systems and the proliferation of neuroimaging-based trials.13
In alignment with the Stroke Roundtable Consortium guidelines, recovery phases were categorized as: acute (<7 days), subacute (7 days to 6 months), and chronic (>6 months). These temporal divisions are crucial for interpreting neuroplasticity results, as the brain’s biological receptivity to intervention changes significantly over time.15
Studies were eligible for inclusion if they met the following criteria: (1) adult participants (aged ≥18 years) with a confirmed diagnosis of ischemic or hemorrhagic stroke; (2) interventions involving electromechanical or robotic devices for lower-limb gait or balance training; (3) a comparison group receiving conventional overground gait training or standard-of-care physiotherapy; and (4) the reporting of outcomes related to motor function (e.g., gait speed, balance) or neuroplasticity (e.g., brain activation, connectivity, spinal reflexes).2
Exclusion criteria were applied to studies that focused solely on upper-limb robotics, those lacking a non-robotic control group (unless they were focused on comparing different robotic modalities), and those involving participants with non-vascular brain injuries unless the data for stroke subjects could be clearly disaggregated.13
Data were extracted from the included studies regarding participant characteristics (age, stroke phase), intervention parameters (type of robot, duration, frequency, intensity), and primary outcomes.2 For the synthesis of neuroplasticity findings, specific attention was paid to the imaging or electrophysiological modalities used and the direction of neural changes reported (e.g., increased activation, enhanced connectivity, normalized frequency spectra).6,16 The keywords were used with Boolean operators to generate the following MeSH terms: Robotics OR Orthotic Devices AND Recovery of Function AND Locomotion AND Motor Skills AND Neuroplasticity. The eligible articles were titled and abstract screening done by three independent reviewers. The final consensus on the selected articles was taken from an additional two reviewers after full text articles were retrieved. To reduce the risk of bias the study quality was independently assessed on Likert scale ranging from 1 to 10. An average score of 6 was taken as cut-off for final selection of the studies from 5 independent reviewers.
All primary studies included in this review were verified for ethical compliance, including approval from respective Institutional Review Boards and the procurement of informed consent from all human subjects.13 This systematic review, as a synthesis of existing literature, did not require separate ethical approval but adhered to the principles of scientific integrity and transparency in data reporting.
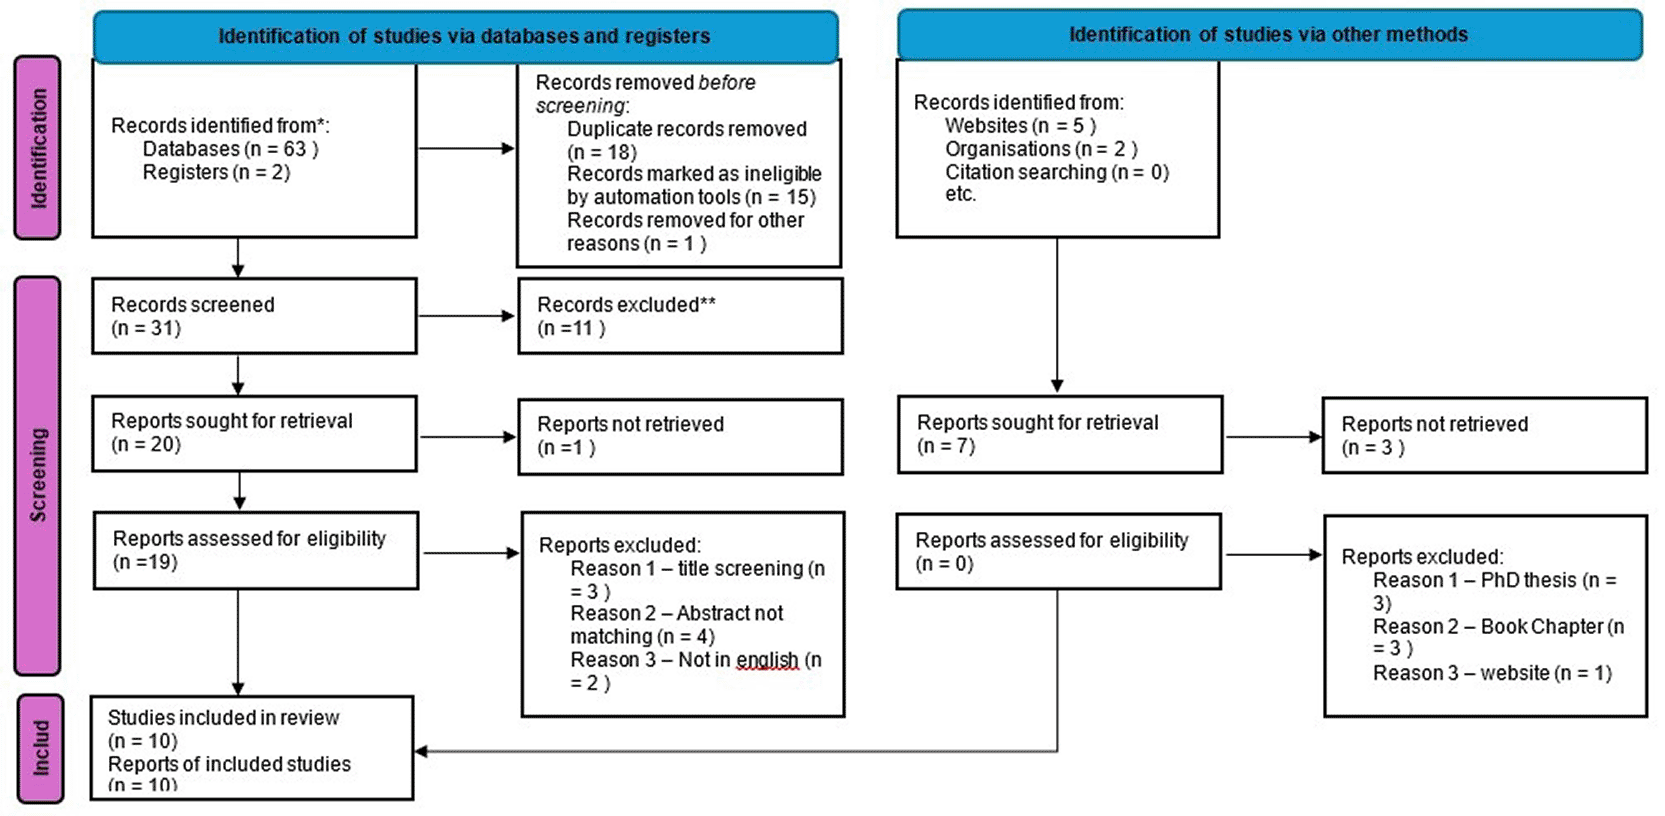
The collective evidence from 2015 to 2025 demonstrates that RAGT is a powerful adjunct to conventional stroke rehabilitation. The details of study extracts, their inclusion and exclusion are given in the PRISMA flowchart (Figure 1).
A 2025 meta-analysis of 23 randomized controlled trials (n = 907) provided the most robust evidence to date regarding functional recovery2 is given in below Table 1.
The exceptionally low heterogeneity for balance improvements (I2 = 2%) indicates that robotic systems provide a highly consistent and reliable stimulus for postural stability across diverse patient populations.2 The improvements in gait speed were most pronounced when interventions were limited to ≤15 sessions, suggesting that early gains in kinematics may plateau without subsequent increases in training complexity or duration.2
A central focus of research during the 2015–2025 period was the identification of neuroimaging biomarkers that correlated with RAGT-induced recovery. Studies using fNIRS and fMRI have consistently identified specific regions of the motor cortex that respond to robotic stimuli.6
3.2.1 Regional activation patterns
Robotic training facilitates a more robust activation of the motor-related cortices in the affected hemisphere compared to conventional overground walking. This reorganization is particularly evident in the primary motor cortex (M1), the supplementary motor area (SMA), and the premotor cortex (PMC)6 which is described in below Table 2.
3.2.2 Functional network topology
Recent studies leveraging graph theory analysis of fMRI data have shown that RAGT promotes “whole-brain” network reorganization.2,6 Successful robotic interventions are associated with the normalization of network metrics, such as a shortened average path length and improved global efficiency.6,16 These changes suggest that the brain’s functional network reverts toward “small-world” properties, which are characterized by high local aggregation and efficient long-distance communication.16
Quantitative EEG (QEEG) has emerged as a valuable tool for measuring the “cortical preparatory state” and spectral power changes after robotic therapy. A significant finding across multiple studies is the reduction of pathological slow-wave activity.6
Power Ratio Index (PRI) and Delta/Alpha Ratio (DAR): RAGT significantly reduces the PRI—calculated as (delta + theta)/(alpha + beta)—and the DAR in the PMC, SMA, and M1. These reductions are negatively correlated with Fugl-Meyer Assessment (FMA) scores, indicating that as the electrophysiological frequency spectrum moves toward high-frequency (alpha/beta) dominance, motor function improves.6
Alpha-Band Coherence: A 2025 study demonstrated that RAGT, especially when combined with electroacupuncture, enhances coherence between the somatosensory association cortex (electrode CZ) and motor planning areas (FCZ, FC2).12 This enhanced connectivity suggests a more efficient transfer of sensory information to motor planning centers.
Event-Related Desynchronization (ERD): Changes in ipsilesional beta-band ERD and synchronization (ERS) have been observed following RAGT, reflecting the normalization of cortical excitability during voluntary leg movements.17
The neuroplastic effects of RAGT extend to the spinal cord, where repetitive stepping patterns influence the locomotor circuitry.
H-Reflex Modulation: Body weight-supported RAGT has been shown to re-establish the physiological phase modulation of the soleus H-reflex.18 In healthy individuals, the H-reflex is depressed during the swing phase to allow for ankle dorsiflexion; in stroke patients, this modulation is often lost, leading to spasticity and foot drop. RAGT helps restore this depression at the stance-to-swing transition, fostering a more natural step progression.18
Operant Conditioning: Studies on volitional down-regulation of the H-reflex show that stroke survivors can achieve an 80% success rate in reflex suppression when given real-time robotic feedback.18 This down-regulation is strongly correlated with improvements in gait symmetry and velocity.18
BDNF is a primary mediator of activity-dependent neuroplasticity, yet its response to RAGT in human stroke patients remains complex.
Circulating Levels: Systematic reviews suggest that aerobic exercise and functional tasks with RAGT promote changes in central BDNF concentrations, although serum levels may not always reflect these shifts.19 A subtle but consistent negative influence is observed in patients carrying the Val66Met polymorphism, who may exhibit slower rates of learning and functional recovery.1
Peripheral Epigenetic Changes: Recent research has identified that while circulating protein levels may remain stable, resisted training with RAGT and aerobic exercise can induce differential DNA methylation of gene in paretic skeletal muscle, potentially regulating the local expression of growth factors.20
The architectural design of the robotic system significantly influences the neuroplastic and functional outcomes, as given in the below Table 3.
| Device Type | Mechanism | Superior Outcomes |
|---|---|---|
| End-Effector (e.g., Loko help, Gait Trainer) | Distal drive (feet); free hip/knee movement | Higher rates of independent walking; superior in subacute phase; consistent gait speed gains.2 |
| Exoskeleton (e.g., Lokomat) | Proximal drive (joints); rigid kinematic guidance | Better for non-ambulatory/severe patients; improved proximal muscle control; high variability in gait speed.2 |
End-effector systems allow for greater movement variability and “destabilization training,” which forces the patient to engage in active motor planning and error correction—two critical components of neuroplasticity.21 Conversely, exoskeletons are superior for early mobilization of severely impaired patients who require total assistance to maintain an upright posture.
The findings from 2015 to 2025 reinforce the fundamental principle of neurorehabilitation: recovery is a dose-dependent process. The primary advantage of robotic systems is their ability to bridge the “repetition gap” that exists in conventional therapy.5 Data from end-effector-based RAGT shows that patients increase their step count from an average of 1,098 in the first session to over 1,500 in the final session—a 39% increase in training volume over a standard six-week program.5 This high volume of stepping is essential for overcoming the threshold required to induce long-term potentiation in the motor cortex.5
Furthermore, the “assist-as-needed” paradigm—where the robot only provides support when the patient’s performance falls below a certain threshold—has been shown to be more effective than continuous passive guidance.21 This is because neuroplasticity is driven by the correlation between volitional motor intent and sensory feedback.16 Passive movement alone may maintain joint range of motion, but it fails to trigger the significant metabolic and electrical changes in the motor planning areas (SMA and PMC) seen during active robotic training.6
The effectiveness of RAGT can be understood through two complementary mechanisms. The “bottom-up” approach utilizes repetitive, high-volume sensory input from the lower limbs to reorganize spinal circuits and stimulate the somatosensory cortex.16,21 By simulating a near-normal gait cycle with standardized plantar pressure and proprioceptive feedback, RAGT reinforces the existing neural pathways and promotes the recruitment of alternative pathways (e.g., the corticospinal tract from the non-lesioned hemisphere).16
The “top-down” approach targets the brain’s executive and planning functions. By integrating RAGT with virtual reality (VR), clinicians can manipulate the visual and cognitive environment to demand higher levels of attention and spatial awareness.9,10 Studies have shown that VR-enhanced RAGT leads to greater improvements in walking speed and balance-related gait metrics compared to robotic training alone, likely due to the activation of prefrontal and parietal regions involved in multisensory integration.9
The timing of rehabilitation initiation is the most critical clinical modifier of neuroplasticity. The strongest effect sizes for RAGT (SMD = 0.74 to 0.75) are found in the acute and subacute phases, while chronic stroke survivors show more limited, though still significant, improvement (SMD = 0.23). This disparity highlights the “neuroplastic window”—a period of several months post-stroke where the brain is biochemically and structurally more receptive to reorganization.9
Early RAGT initiation (within 3 months of onset) has been shown to accelerate bi-hemispheric reorganization in motor-related brain regions and reduce the length of stay in rehabilitation facilities.12 In contrast, in the chronic stage, neuroplasticity is often exhausted or stabilized, requiring more intensive or longer-duration interventions (e.g., >6 weeks) to achieve meaningful functional changes.8
One of the most promising trends in the last decade is the combination of RAGT with other neuromodulatory techniques such as tDCS.
Non-invasive Brain Stimulation (NIBS): Combining RAGT with repetitive Transcranial Magnetic Stimulation (rTMS) or Transcranial Direct Current Stimulation (tDCS) has shown synergistic effects. Specifically, low-frequency rTMS applied to the unaffected hemisphere can reduce maladaptive interhemispheric inhibition, “priming” the affected hemisphere to respond more effectively to the sensorimotor training provided by the robot.4
Electroacupuncture (EA): The integration of EA with RAGT has been shown to improve the functional connectivity of the brain network more effectively than either treatment alone. The findings suggest that EA may reverse the pathological frequency spectrum imbalance seen after stroke, aiding the neural network in re-entering an efficient information-processing state.12
Despite the evidence for its neuroplastic potential, several barriers to the widespread adoption of RAGT remain.
1. Heterogeneity of Protocols: There is currently no clear consensus on the optimal “dose” of RAGT. Trial protocols vary widely in terms of session duration (30 to 60 minutes), frequency (3 to 5 times per week), and total sessions (15 to 40).22
2. Cost and Accessibility: The high up-front and ongoing costs of robotic systems must be balanced against long-term gains in patient independence and the reduction of caregiver burden.10 Reducing the high upfront costs is essential for ensuring that these innovative health infrastructures are available to diverse patient populations, thereby reducing the long-term societal cost of disability.
3. Chronic Phase Efficacy: While RAGT can benefit chronic patients, the magnitude of the effect is smaller, suggesting that “maintenance” or “booster” protocols may be needed to sustain initial gains.3
4. Individualized Response: Genetic factors, such as the BDNF Val66Met polymorphism, and clinical variables like the location and extent of the brain lesion, contribute to high inter-patient variability in the neuroplastic response.1
The literature from 2015 to 2025 established robot-assisted gait training as a cornerstone of technology-enhanced neurorehabilitation. RAGT facilitates significant functional recovery in stroke survivors, particularly in the domains of balance and gait function, by providing a high-volume task-specific stimulus that far exceeds the intensity of conventional physical therapy. This mechanical stimulus is translated into neurological reorganization through the activation of key motor planning areas, normalization of cortical frequency spectra, and modulation of spinal locomotor circuits.
The findings underscore the importance of early intervention, as the subacute phase represents the most fertile ground for neuroplastic changes. Furthermore, the evidence supports a nuanced approach to device selection, with end-effector systems showing particular effectiveness in improving gait speed and independence, whereas exoskeletons remain vital for the mobilization of severely impaired individuals. As the field progresses, the integration of RAGT with adjunct technologies, such as neuromodulation and virtual reality, alongside the use of advanced biomarkers to tailor interventions, will likely be the next step in achieving personalized and profound neurological restitution for stroke survivors. The integration of RAGT represents a significant step toward personalized and sustainable neurorehabilitation. By optimizing the timing and dosage of intervention, clinicians can contribute to the global goal of enhancing well-being and functional independence for the growing population of stroke survivors. Future research must focus on determining the optimal longitudinal dosage and long-term sustainability of these robotically induced neural changes.
The study was conducted in line with the Declaration of Helsinki and approved by the Dubai Scientific Research Ethics Committee (DSREC), Dubai Health Authority (MBRU IRB-2024-417), Dubai, UAE, for ethical clearance.
Not Applicable.
Figshare. RTNS-REVIEW. https://doi.org/10.6084/m9.figshare.32064228.23
The project contains the following underlying data:
• DSREC-DECISION_Student_MBRU IRB-2024-417 [Ethical Approval Letter]
• PRISMA_2020_checklist
Data is available under the terms of the CC BY 4.0.
The author(s) declared that no grants were involved in supporting this work.
© 2026 Manickavasagam I et al. This is an open access article distributed under the terms of the Creative Commons Attribution License, which permits unrestricted use, distribution, and reproduction in any medium, provided the original work is properly cited.
Download
Export To
metrics
| Views | Downloads | |
|---|---|---|
| F1000Research | - | - |
| PubMed Central Data from PMC are received and updated monthly. | - | - |
Citations
CITE
how to cite this article
Manickavasagam I, Srinivasan V, Durairaj S et al. Robotic Training and Neural Reorganization in Stroke: A Systematic Review [version 1; peer review: 2 approved]. F1000Research 2026, 15:762 (https://doi.org/10.12688/f1000research.180596.1)
NOTE: If applicable, it is important to ensure the information in square brackets after the title is included in all citations of this article.
track
receive updates on this article
Track an article to receive email alerts on any updates to this article.
Current Reviewer Status: ?
Key to Reviewer Statuses VIEW HIDE
ApprovedThe paper is scientifically sound in its current form and only minor, if any, improvements are suggested
Approved with reservations A number of small changes, sometimes more significant revisions are required to address specific details and improve the papers academic merit.
Not approvedFundamental flaws in the paper seriously undermine the findings and conclusions
Version 1
VERSION 1
PUBLISHED 19 May 2026
Reviewer Report 28 Sep 2026
Rajan Balakrishnan, MAHSA University Malaysia, Selangor, Malaysia
Approved
VIEWS 0
Are the rationale for, and objectives of, the Systematic Review clearly stated?
Yes
Are sufficient details of the methods and analysis provided to allow replication by others?
Yes
Is the statistical analysis and its interpretation appropriate?
Yes
Are the conclusions drawn adequately supported by the results presented in the review?
Yes
If this is a Living Systematic Review, is the ‘living’ method appropriate and is the search schedule clearly defined and justified? (‘Living Systematic Review’ or a variation of this term should be included in the title.)
Yes
References
1. Koldaş Doğan Ş: Robot-assisted gait training in stroke. Turkish Journal of Physical Medicine and Rehabilitation. 2024; 70 (3): 293-299 Publisher Full TextCompeting Interests: No competing interests were disclosed.
Reviewer Expertise: Physiotherapy
CloseReviewer Report 08 Jul 2026
S. Jeyakumar Jeyakumar, Garden City University, Bangalore, Karnataka, India
Approved
VIEWS 0
Are the rationale for, and objectives of, the Systematic Review clearly stated?
Yes
Are sufficient details of the methods and analysis provided to allow replication by others?
Yes
Is the statistical analysis and its interpretation appropriate?
Yes
Are the conclusions drawn adequately supported by the results presented in the review?
Yes
If this is a Living Systematic Review, is the ‘living’ method appropriate and is the search schedule clearly defined and justified? (‘Living Systematic Review’ or a variation of this term should be included in the title.)
Yes
Competing Interests: No competing interests were disclosed.
Reviewer Expertise: Geriatrice rehabilitationa and stroke rehabilitation.
CloseAlongside their report, reviewers assign a status to the article:
| Invited Reviewers | ||
|---|---|---|
| 1 | 2 | |
| Version 1 19 May 26 | read | read |
Sign up for content alerts
Alongside their report, reviewers assign a status to the article:
Approved - the paper is scientifically sound in its current form and only minor, if any, improvements are suggested
Approved with reservations - A number of small changes, sometimes more significant revisions are required to address specific details and improve the papers academic merit.
Not approved - fundamental flaws in the paper seriously undermine the findings and conclusions